WH-380-F, certifying for a family member
Your patient’s clinic visit is ending when her daughter surprises you with a copy of the WH-380-F, the FMLA form for time off to care for a family member, and asks if you can fill it out for her now. Your clinic is running behind, and you know that if the form is filled out incorrectly, the daughter’s leave may be delayed. What do you do?
 Kevin Lease, MD·Internal medicine, primary care·September 2026
- Form
- WH-380-F, Certification of Health Care Provider for Family Member’s Serious Health Condition
- Issued by
- U.S. Department of Labor, Wage and Hour Division
- Blank form
- WH-380-F PDF on dol.gov
- Revision
- June 2020
- OMB control number
- 1235-0003, expiration printed as 8/31/2029
- Your patient
- the family member who is ill, not the employee
- Return to
- the patient, never the Department of Labor
Key points
- Section II is the employee’s, you don’t fill it out. Your part is Section III, pages 2 to 4.
- Unclear about any details concerning the leave request? Schedule a visit with your patient and the caregiver within a couple of days.
- The item numbers differ from the WH-380-E. Condition type is item 5, episodes item 10.
- Item 4 is the heart of the form. Describe the care your patient needs, not the diagnosis.
- Item 10: how often and how long each time. One without the other may not be accepted.
- Certify your patient only. Nothing about other family members, and nothing genetic.
- There is no Part C. This form is about time to care for someone, not the employee’s job.
Once you know what HR (Human Resources) needs from each item, PatientPapers, the app I built, can fill in your part of the Department of Labor's WH-380-F for you to review and sign.
Try a sample FMLA form WH-380-FWhen the form arrives at the wrong moment
When the daughter hands me the form at the end of her mother’s clinic appointment, I would begin with some questions: what is the leave for? Even when the answer is the problem we just spent the visit on, there is probably more information needed to complete the form that the visit might not have covered, such as what her mother needs help with and how often the daughter has to be there. Some kinds of leave ask for even more information. Basically, in that situation, where it looks like it’s going to take more than five minutes and I’m behind, I would tell her something like: “I’m sorry, I’d like to get this done for you right now, but that takes more time for additional questions than today’s visit leaves room for, otherwise I’m afraid the form won’t be done correctly and your HR might not accept it. I have some other patients waiting for me right now. Can we please schedule your mother a visit with you present in the next couple of days, just to make sure this form gets filled out correctly?”
More often the form is actually left at the front desk by the relative who wants the leave, with nothing to say what the leave is for. What I know about my patient is based on their last visit, which could have been a while ago. If things have changed since, or the reason for the leave never came up that day, it would be impossible for me to accurately complete the form. Families rarely understand what information is needed for me to complete the form, and typically the front-desk staff don’t know that either.
On this form, the person who knows the answers best is often not your patient but the caregiver. The daughter is the one helping her mother bathe, driving her to therapy, and getting the call when she falls. She knows what help is needed, how often, and for how long each time, and those are the answers that get the leave approved. In my experience, you need that conversation to fill out the form correctly, and in person is best. So when the form is dropped off without that information, have your staff schedule a visit for your patient and ask the caregiver to come too, with your patient’s permission. If the caregiver cannot come, ask them to complete their own section of the form (Section II) and send a short written note: the help your patient needs, how often, and how long each time. A note from the person doing the care can fill in gaps that would not be possible to reconstruct from a chart review in most cases.
You can save yourself a lot of headaches by teaching your front-desk staff that when a relative drops off FMLA paperwork, they should explain that a visit is needed to successfully complete it, with the caregiver wanting leave in attendance. If possible, have them schedule it within a couple of days, since the return date in Section I, item 3, is counted from the date HR requested the form, not from when it reached your office.
Be careful, it’s easy to mix up the people on the form fields
The WH-380-F is the Department of Labor’s form for an employee who needs time off to look after a family member who is ill. This guide covers the medical part. Whether the leave is protected also depends on the employer being covered, the employee being eligible and the employee having leave left, and HR decides that. On the WH-380-E the patient and the employee are the same person. Here they are not, and almost every difference between the two forms comes from that one fact.
The employee is the person who works somewhere, wants time off, and brought you the form. While you may never meet them, it makes it a lot easier if they are present when you complete the form. The patient is your patient, the one who is ill; their condition is what the form is about, and they are not the one asking an employer for anything. You certify the patient’s condition and the care that patient needs.
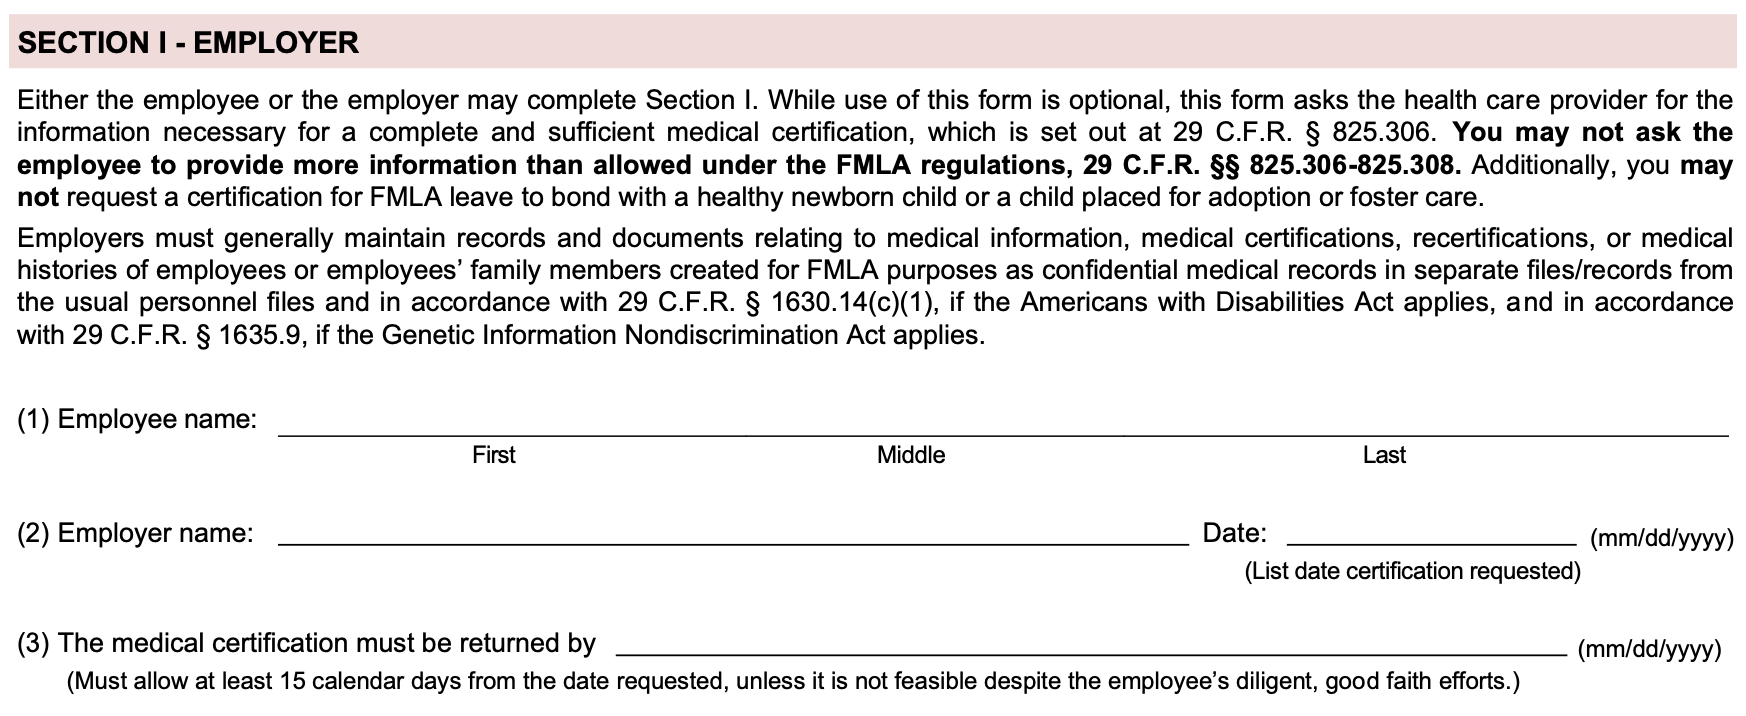
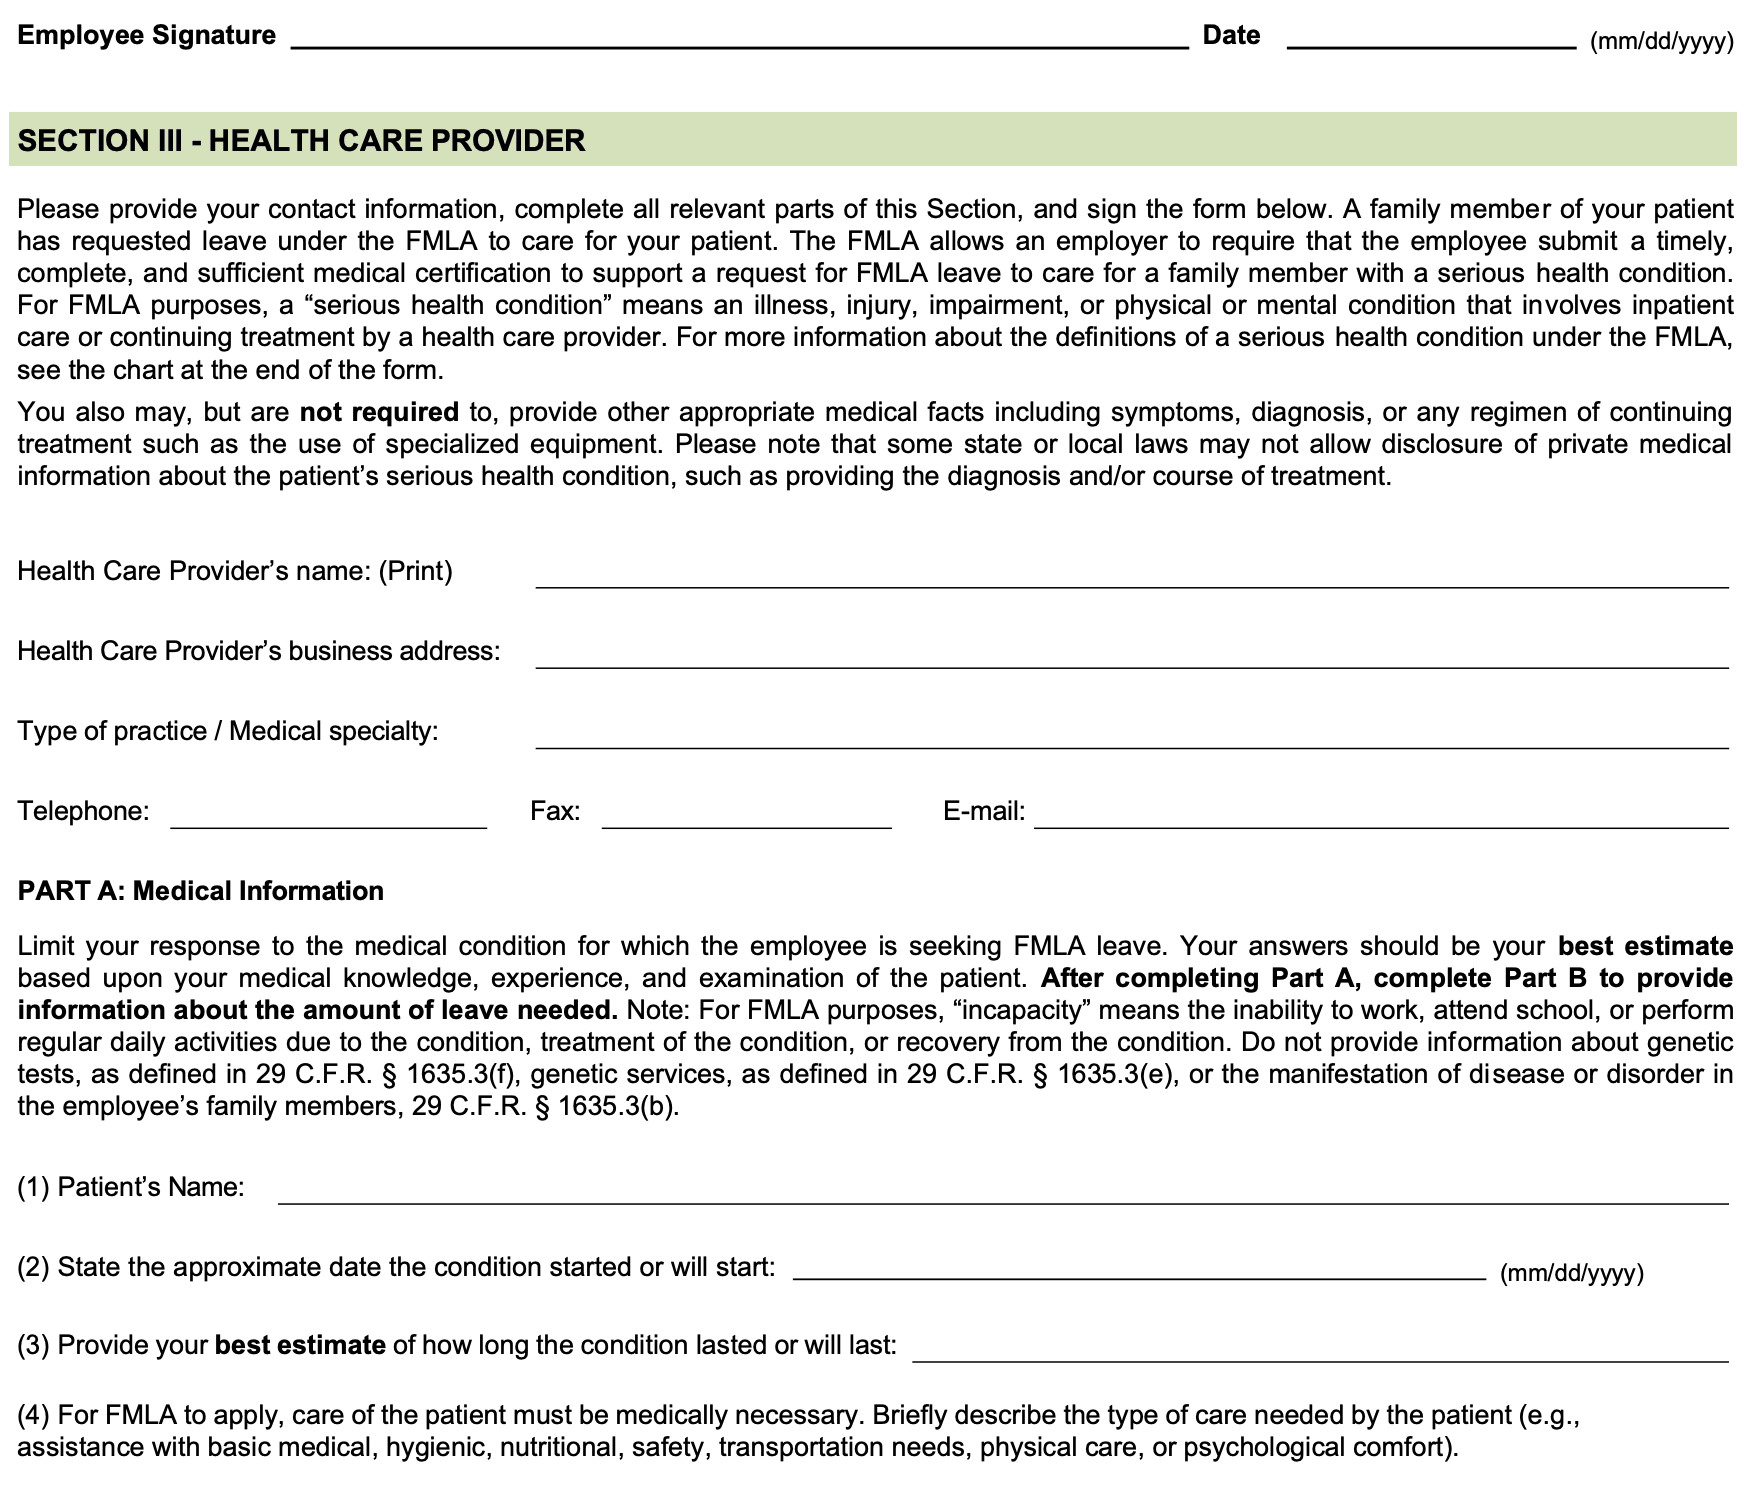
The form is four pages in length and is comprised of three sections. Either the employee or the employer may complete Section I on page 1, and it carries no job title, hours or job description, because whether the employee can do their job is not the question here. Section II is for the employee to complete, and it runs from page 1 onto page 2, ending with their signature. Section III is for the clinician to complete. It starts at the green bar partway down page 2 and runs to your signature on page 4.
Once Human Resources (HR) asks for the form, the employee must hand it in by the date in Section I, item 3. The form says that date must allow at least 15 calendar days from the date requested, unless it is not feasible despite the employee’s diligent, good faith efforts. If that date is blank, I would leave it for the employee or HR to fill in, and mention it to the family. If HR finds an answer missing or too vague, the form won’t be accepted and it comes back with seven calendar days to correct it, unless that is not practicable despite the employee’s diligent, good faith efforts. A corrected form that still falls short could end with the leave denied. A returned form is harmful in several ways: it takes more time for the daughter to deal with, it takes more of your time for a second pass, and at worst it could cost her the leave.
When both of them are your patients. Sometimes you care for the mother and the daughter. The question to ask is whose condition is keeping the daughter from work. If she needs time off to care for her mother, that is this form, the WH-380-F, and it is about her mother’s condition. If the daughter herself becomes ill, say she is depressed from the strain of caregiving and is missing work because of her own symptoms, that is a separate form, the WH-380-E, about her own condition, filled out at her own visit. Keep the two apart: nothing about the daughter’s health goes on her mother’s form, and nothing about the mother’s health goes on the daughter’s. Both kinds of leave usually come out of the same 12 weeks.
To see this form filled in for four fictional families, a parent with dementia, a child on chemotherapy, a spouse after a stroke and an adult child with diabetes, see WH-380-F examples.
The rule: 29 C.F.R. §§ 825.200, 825.305, 825.306, 825.313.


Section II: the employee’s part, and why you leave it alone
You need to recognize Section II so you know when it is missing, not so you can fill it in. The employee writes the name of the family member they will care for; they check the appropriate box to indicate their relationship (spouse, parent, child under 18, or a child 18 or older who cannot look after themselves because of a disability); select the appropriate box to indicate the kind of care they will provide (help with basic medical, hygiene, nutrition or safety needs; transport; physical care; psychological comfort; or other); estimates how much time off they need; and, if they need a shorter working week rather than time away, writes the hours per day and days per week they can work. Then they sign and date it.
Notice that last one. On the WH-380-E, you certify a reduced schedule. On this form the employee states it themselves; it is not yours to complete.
If Section II is filled in, read it before you write anything in your own section. The employee has checked boxes for the kind of care they will give, and your answer in item 4 should not contradict them. I explain why under item 4.
Sometimes Section II arrives blank. Leave it that way. Don’t fill it in yourself, and don’t have your staff call the employee to get the answers. Section II is the employee telling their employer how they are related to your patient, and only the employee can make that statement. You usually can’t confirm it anyway. You may not know whether two people are married, and the form counts someone as a parent or child even without a legal or biological tie, which isn’t a medical question. Fill out your part, Section III, as usual. Then give the form back and tell your patient that the employee has to complete and sign Section II before it goes to the employer.
The rule: 29 C.F.R. §§ 825.122, 825.305.
Section III: your contact block
Write your name exactly as you’ll sign it on page 4, then the practice’s address, phone, fax and email, and your type of practice or specialty (family medicine, say, or orthopedic surgery). If HR needs to confirm you filled the form in, or to ask what one of your answers means, this is how they’ll reach you.
Item 1: the patient’s name
Write your patient’s name: the person who is ill, the one in front of you. Not the name of the employee/caregiver who is missing work to provide care.
The trap is the header. Pages 2, 3 and 4 each open with a line marked “Employee Name”, and putting the patient’s name there instead of the employee’s name is, in my experience, the most common mistake clinicians make when they fill out the WH-380-F. Employee Name is the family member who works. Patient’s Name, here in item 1, is your patient. Getting the two the wrong way round makes the whole form look unread.
Item 2: when did the condition start?
Give your best estimate of when your patient’s condition started, or when it will start. The month and year is enough, and for something that has been going on for years, “approximately 2019” is fine.
Item 3: how long will it last?
This question is about how long the condition will last, not how much time off the employee needs. Give a range in weeks or months, such as “six to eight weeks” or “three to six months.” If the condition will not go away, I would write “Lifelong; this certification covers the next 6 months”, as long as Part B (items 7 to 10) gives the time off, such as one continuous stretch in item 9, or how often and how long each time in item 10. That says what is true of the condition, so the paper doesn’t claim a lifelong disease lasts six months, and it also gives HR a period to plan around. For one that may ease with time, such as migraine, I would write “Long-term; this certification covers the next 6 months”. Long-term here does not mean the permanent or long term box in item 5. Keep in mind that when the need for leave continues, HR can ask for the form to be recertified, no more than every 30 days and in connection with an absence. If the shortest length I certify is longer, HR waits that long, up to six months, unless leave is extended, things change or something casts doubt on the form.
Avoid “unknown”, “indeterminate”, or “lifetime” or “ongoing” on their own in this box. HR reads your answer to plan how much time off to approve, and “unknown” or “indeterminate” gives them nothing to build a schedule or a staffing plan around. “Lifetime” may be true of the condition, but alone it still tells HR nothing they can plan with, which is why I add the period I am certifying. That is my practice, not something the form requires. Any of these may mean HR does not accept the form and asks you to clarify.
The rule: 29 C.F.R. § 825.308.
Item 4: what care does your patient need?
This box has no equivalent on the WH-380-E, and it is the reason this form exists. The first sentence printed in it is the legal test: for the leave to apply, care of the patient must be medically necessary. On the employee’s own form, the WH-380-E, you certify that the employee cannot work. Here, on the WH-380-F, you certify that your patient needs someone.
It’s best to describe the care needed, not the diagnosis. “Status post stroke with residual left-sided weakness” is a fine clinical sentence and it answers the wrong question: it says what is wrong with your patient, not why the daughter has to be somewhere other than work. The form hands you the vocabulary in its own example list, and those words are worth using because they match the boxes the employee checked in Section II: help with basic medical, hygiene, nutrition or safety needs; transport; physical care; psychological comfort. For the patient above: “Requires help with bathing, dressing and taking medication; cannot drive and needs transport to physical and occupational therapy three times a week; needs supervision for safety because of fall risk and impaired judgment.” Every phrase is something a person has to be physically present to do.
Clinicians might not be aware that psychological comfort is a type of care that is covered under FMLA when the patient is receiving inpatient or home care. For example, if your patient needs a familiar person there, such as someone with dementia who becomes agitated and is unsafe alone, or someone in the last stage of an illness, those would be legitimate cases where the caregiver taking leave from their work to provide psychological comfort to the patient would be covered.
Leave is also covered for time the employed family member needs to spend arranging care for your patient. For example, coordinating a move into a nursing home would be covered. In addition, if the patient’s usual caregiver can’t be present, time spent filling in is covered, too. The employee doesn’t have to be the only person available, and shared care still counts.
You should read Section II first before doing item 4 to see what the employee checked as the care they will provide, and make sure your item 4 does not contradict it. If the daughter checked transport and physical care and you write “independent in daily activities”, that may cause her leave not to be covered, not because either of you misstated the facts, but because the two parts were incongruent. You are not obliged to agree with what the caregiver writes. You definitely should not attest to something that you do not believe, as it is your signature and your reputation on the line. To give an example, if the honest answer is that the patient “needs help with transport, not with physical care”, write exactly that. This highlights another benefit of meeting with the patient and caregiver face to face, to be able to have an honest discussion about your impressions about the caregiver’s stated reasons for the leave, whether you agree that for the patient’s condition the care is medically necessary, explaining the criteria of FMLA leave, what you are comfortable attesting to and sharing that feedback with the caregiver and patient to help manage their expectations.
The rule: 29 C.F.R. § 825.124.

Item 5: which kind of condition is it?
What “incapacity” means here. On this form, incapacity means your patient cannot work, go to school, or carry on normal daily life because of the condition, its treatment, or recovery from either. Your patient does not need a job for this to apply. A nine-year-old with pneumonia who cannot go to school is incapacitated. So is a retired father after a hip replacement who cannot bathe, dress or get to his appointments without help. Each is a reason a family member may need time off to be there to help.
Item 5 of the WH-380-F is the WH-380-E’s item 3 under a different number. It’s still the same six kinds of conditions, and the patient has to meet the criteria of one of the six boxes. A patient admitted overnight fits “Inpatient Care.” A patient who couldn’t get through their normal day for more than three full calendar days in a row, and was seen by a clinician for it, may fit “Incapacity plus Treatment.” Check every box that applies and then complete the lines beneath it. Those fields are the evidence to support the selected box or boxes. Failure to fill in the supporting information on the lines provided is one of the chief reasons these forms are not accepted. Whatever box or boxes you select here, their time impact has to be documented in Part B.
Don’t let the box names confuse you. They read like diagnoses, but basically they sort time, not disease. If you asked me as a physician whether diabetes is chronic or permanent, I would answer that, to me, diabetes fits both terms. This form is somewhat counterintuitive for a physician, because the diagnosis doesn’t decide which box you check. How the condition affects your patient’s normal day does. For each box, the question isn’t whether the disease matches the name, but whether the box describes how the illness is keeping your patient from their normal day. One patient’s situation can fit several boxes at once, and then you check each one that fits. Consider a father who had a stroke with partial left-sided weakness. He could have a week in the hospital, then a skilled nursing facility, then outpatient physical therapy three times a week, with someone at home for good because unfortunately the deficits didn’t improve enough to live safely without the extra help. That’s inpatient care, multiple treatments, and permanent or long-term, and all three boxes can be checked. Here they are in the order the form prints them:
Most of the items on this form start with a choice of tense, such as was or will be, and your patient has been or is expected to be. I would check every one that applies, so if your patient has been off since last week and will stay off, check both. If you are filling in the form before a planned operation, check “is expected to be” and “will be”, and give the dates you expect.
| Box | Check it when the time lost looks like this | Then fill in |
|---|---|---|
| Inpatient care | One stretch built around an overnight stay in a hospital, hospice or residential care facility, past or scheduled. Days your patient couldn’t manage their normal day because of the same illness count as part of that stretch, whether they came before the admission or during recovery at home afterwards. | The admission date or dates. The whole stretch, recovery included, goes in item 9. |
| Incapacity plus treatment | One stretch of more than three full calendar days in a row when your patient could not get through their normal daily activities, from an illness or procedure that then ends: an outpatient surgery, a bad infection. Partial days alone do not count. They also had two in-person visits for treatment within 30 days of the first day of incapacity, with the first of those visits within 7 days of that day, or one in-person visit within 7 days that started ongoing treatment. A telemedicine visit counts as in person, the Department of Labor says, if it includes an exam, evaluation or treatment, your state licensing authorities permit and accept it, and generally it should be by video. A phone call, letter, email or text alone does not count. (Field Assistance Bulletin 2020-8.) A second visit can fall after the 30 days if something outside the family’s control, such as no open appointments, kept it from happening as you planned. The rule says the employee’s control, and I read that to cover my patient’s visit here. The 7-day first visit has no such exception. If the dates don’t fit for any other reason, I would not check this box. Those are the patient’s days, not the employee’s days off work. Short spells of incapacity from a recurring problem do not fit here; see chronic conditions. | The first and last days of the stretch, the visit dates, and whether ongoing treatment started. The time goes in item 9. |
| Pregnancy | Any time the pregnancy keeps your patient from their normal day: prenatal visits, severe morning sickness, prescribed bed rest, delivery and recovery. There is no minimum number of days, and a day your patient is incapacitated counts even if they were not seen that day. | The expected delivery date. Prenatal visits go in item 7, unpredictable days of incapacity in item 10, delivery and recovery in item 9. |
| Chronic conditions | Spells of incapacity that come and go over months or years, with your patient managing normally in between: an asthma attack, a seizure, a run of unstable blood sugars. The condition needs a clinician at least twice a year. Each lost day counts on its own, with no minimum number of days and no visit needed that day. | Nothing on these lines. How often your patient is incapacitated, and for how long each time, goes in item 10. |
| Permanent or long-term conditions | Permanent or long-term incapacity from a condition treatment may not help, under a clinician’s continuing supervision even when no active treatment is under way: advanced dementia, the terminal stages of cancer, a stroke with lasting deficits. | Nothing on these lines. A long stretch goes in item 9, and any unpredictable extra days in item 10. If there is no block of time with an end date and the employee’s absences come and go, leave item 9 blank and put them in item 10. |
| Conditions requiring multiple treatments | Here the time off is for the treatments themselves, such as chemotherapy, radiation, dialysis, or a series of physical therapy visits. Your patient may manage fine between sessions but need someone to get them there and back. It covers restorative surgery after an accident or injury, or any condition that would keep your patient from their normal day for more than three full calendar days in a row if it went untreated. | Nothing on these lines. The treatment dates or schedule go in item 7, or item 8 if you referred them elsewhere. If the employee has to be away for those trips, that time goes in item 10 too. |
What counts as ongoing treatment? For the incapacity plus treatment box, it means care you prescribed and are following, such as a prescription medication, even one course of an antibiotic, a course of physical therapy or a piece of medical equipment. Rest and over-the-counter remedies can be appropriate medical advice, but on their own they don’t meet the requirement of this section of the form.
Chronic, or permanent and long-term? These two are easily confused. The decision is actually the pattern of the days of incapacity, not whether the disease will ever go away. A mother with heart failure who manages okay most days but has occasional flare-ups causing incapacity that requires the family member’s help at those times would fit “chronic” better than “permanent or long-term”, even though her heart failure will not resolve. Permanent or long-term is for a long or permanent period of incapacity, rather than spells, from a condition treatment may not help. For example, if, despite optimal medical therapy and interventions, the heart failure symptoms cause daily incapacity requiring daily help from her family member, then “permanent or long-term” would be appropriate.
If none of the six boxes fits, check “None of the above”. Be clear about what it means: you are telling the employer that your patient’s condition does not qualify, and the caregiver’s leave will likely be denied. If that is the honest answer, it is the right one. But do not check it by default: if a box fits, check that box and fill in its lines. And if the answer is no, tell your patient before the form leaves the room.
The rule: 29 C.F.R. §§ 825.113 (incapacity is defined in 825.113(b)), 825.114, 825.115, 825.120(a)(4).
Item 6: anything else worth saying? (optional)
This box is optional. You can add information about your patient’s condition that helps explain the care they need, such as their symptoms, the treatment plan, or equipment like a nebulizer. The form itself says you are not required to add these other medical facts, and it also points out that some state or local laws may limit the diagnosis or course of treatment you can disclose. If a state limits treatment details too, I would check before describing them. For example, my understanding is that California’s own leave law does not require the diagnosis at all. What I do is leave the diagnosis off the form, and instead I describe the symptoms and the care that is scheduled. In my experience that gives HR enough to understand why the leave is needed. It’s the same approach I use for item 4 on the WH-380-E. I write the symptoms, what they keep my patient from doing, and the treatment described as time rather than as a medication name. I also try not to name an organ system if that would give away the diagnosis. My understanding is that mental health conditions, addiction treatment and HIV status are treated as especially sensitive in at least some states, in addition to the federal rules that protect addiction treatment records and psychotherapy notes. If your patient’s condition falls into one of these areas, it is especially important to leave the diagnosis off the FMLA paperwork.
One instruction on this form reads strangely, and it’s worth understanding so you don’t over-correct. Part A tells you not to describe “the manifestation of disease or disorder in the employee’s family members.” Your patient is the employee’s family member, so if you read that sentence literally it would rule out the whole form. That wording appears on the employee’s own form, the WH-380-E, too, and certifying your patient’s condition is the whole reason this form exists. So go ahead and certify it. What should still stay off the form is information about anyone else in the family. The form says not to list genetic tests or genetic services, so no genetic test results or genetic counseling, your patient’s or anyone else’s. I would leave out “strong family history of stroke” and “her son also has high blood pressure” too. Your patient’s condition belongs on the form, but the rest of the family’s health does not. The federal genetic information law limits what employers may ask for, but it makes an exception for family history requested for FMLA certification, so my reason is the form’s instruction.
The rule: 29 C.F.R. §§ 825.306, 1635.3, 1635.8(b)(3); Cal. Gov. Code § 12945.2 and 2 C.C.R. § 11091; 42 C.F.R. Part 2; 45 C.F.R. § 164.508(a)(2).
Item 7: planned appointments
If you know the dates of your patient’s scheduled appointments, write them here. If you don’t, write the pattern instead, for example “physical and occupational therapy three times a week.” The time the employee takes off to bring your patient to these appointments is protected, so listing them helps the employee. Writing “scheduled medical visits” with the dates is a complete answer, and it avoids giving out more health information than the form needs.
Item 8: referrals to other clinicians
If you have referred your patient to someone else, write what the referral is for (for example a medical specialist or physical therapy), the start and end dates of that treatment, and how much time each visit takes. The box says “including any period of recovery.” A lot of clinicians write the treatment dates and stop there, but the recovery time is part of the answer too. Be careful with the name of the specialty, because it can give away the diagnosis. Writing “oncology,” “psychiatry” or “infectious disease” basically tells the employer what is wrong. When naming the referral would reveal the diagnosis, I would suggest describing it as a treatment schedule instead, such as “medical specialist evaluation and treatment, monthly” or “physical therapy, three days a week.” That fully answers what the form asks. If HR does ask for more information, they have to give the employee seven calendar days to respond. They also cannot ask you for anything beyond what the form itself asks. They may contact you only to confirm the form is yours or clarify an answer, after the employee had a chance to fix it. The FMLA itself doesn’t require consent for the first, as I read the rule. But the Department of Labor has said that if confirming means sharing identifiable health information, HIPAA requires a valid authorization. So before I answer HR either way, I want my patient’s authorization, or their representative’s, because the information is my patient’s, not the employee’s. If the form stays unclear because no one gives that permission and the employee doesn’t clarify it another way, HR may deny the leave. And when HR asks for a recertification, it may send you a record of the absences and ask whether that pattern fits the condition, which is a fair question to answer.
The rule: 29 C.F.R. §§ 825.305(c), 825.306(a)(3), 825.307(a).

Item 9: one continuous block of time
If your patient’s condition will keep them from their normal daily activities for one continuous stretch of time, including treatment and recovery, write a start date and an end date. The form is asking for your best estimate. If you really can’t estimate an end date, give a date when you will reassess and explain why in item 6. Leaving the end date blank reads as “unknown,” and that often leads to the form not being accepted. Often you can still estimate. Say your patient is in the hospital with a hip fracture, and whether she goes home or to a rehabilitation facility will be decided at a care meeting next week. I would write the date I think most likely from what I know of her recovery today, and in item 6 write “Length of care needed depends on discharge planning on [date]. I will re-evaluate then.”
Item 10: time off in episodes
Read this one carefully, because it is worded differently from the WH-380-E in a way that matters. It asks whether the employee needs to be away from work, now and then, to look after your patient, including during flare-ups. On the other form you certified that the patient could not work. Here you are certifying that someone else needs to be away from their job because your patient needs them there.
Item 10 asks for two numbers. Over the next six months, estimate how often the episodes will happen (times per day, week or month) and how long each one will last (hours or days). You need both. “2 to 3 times per month, about 1 day per episode, for falls, illness and unscheduled visits” is a complete answer, but “as needed” is not. Giving how often without how long, or how long without how often, is the other common reason the form is not accepted and goes back to the employee to be fixed. It is also fine for a patient to need time in both categories. For example, a patient on dialysis three times a week might also be incapacitated at unpredictable times. The dialysis schedule goes in item 7. If the employee has to be away for those sessions, that time goes here in item 10 too, along with the unpredictable days.
This is where having your patient in the room, and ideally the employee too, matters most. For a chronic condition that flares, ask how often the flares have been coming and how long each one needs the employee there, and settle the numbers together. If you estimate from the chart alone, your estimate may fall short of the care your patient actually needs, and the employee may contact your office to ask for the form to be amended.
And the “lifetime” trap, once more. Your patient’s deficits may well be permanent, but item 10 asks about the next six months. Answer the question in front of you.
Sign on page 4, yourself
Sign and date at the bottom of page 4, with the same name you printed in your contact block. Your medical assistant or front-desk staff cannot sign this. A nurse practitioner or physician assistant who is working within their state’s scope of practice can sign it themselves and does not need to send it on to a physician. And notice what is not there: on the WH-380-E, Part C asked you to name a core part of the job your patient could not do. There is no Part C on this form and no job question at all. You have never met the employee and nobody asked, so do not volunteer an opinion about whether the daughter can do her job.
The employee signs their own line at the end of Section II. A form where the provider has signed the employee’s line is a form that may not be accepted.
Who carries it out of the room
The bottom of page 4 says, in capitals, return it to the patient, never to the Department of Labor. On the WH-380-E that is the end of it: your patient carries their own medical information to their own employer. On this form the completed certification has to reach the daughter’s employer, and the daughter is not the patient. Handing it to her is a disclosure of your patient’s medical information to someone else, and “she is his daughter” is not, by itself, your permission to do that.
My understanding is that the details turn on your state and your practice’s own policy, so raise this with your privacy officer. My practical approach: at the visit where you complete the form, get a signed authorization from the patient, or from whoever properly speaks for the patient, naming the employee and the employer as the people who may receive it. If the patient is a competent adult, it is their information and their call, and it takes ninety seconds while they are in the room. If the patient is a minor child, the parent generally speaks for them and you give it to the parent. If the patient is an adult who cannot decide for themselves, you need to know whether the employee actually holds that authority (guardianship, power of attorney, a health care proxy); the relationship box in Section II is the employee’s statement to their employer, not proof of who may receive records from you. Use your practice’s own authorization form, then note in the chart what you released and to whom.
I give the form back to my patient, as the form says, and I don’t send it to HR myself unless my patient has authorized that in writing. If HR calls afterwards, they may only confirm you filled the form in or ask what an answer means, and never through the employee’s direct supervisor. If someone is fishing for detail you deliberately left out, you can say no.
The rule: 29 C.F.R. § 825.307.
Why it is not accepted: the six usual suspects
- Section II is blank, or the provider filled it in or signed the employee’s line.
- Item 4 describes the diagnosis instead of the care the patient needs, or contradicts what the employee checked in Section II.
- Item 3 says “unknown”, “indeterminate”, or “lifetime” with no period.
- Item 10 has how often but not how long, or the reverse, or says “as needed”.
- A box is checked in item 5 but the lines under it (visit dates, admission date) are empty.
- The patient’s name is in the “Employee Name” header, or the answers were written from memory of the WH-380-E and landed on the wrong item.
If only something small needs to change, you usually don’t need to start a new form. For example, if the flare-ups go from once a month to twice a month, in my experience HR will usually accept the correction made on the original form. Cross out the old answer with a single line, write the new answer next to it, initial and date the change, and give it back to your patient, or to the employee if you have that authorization.
Questions the office asks
What is Form WH-380-F?
Form WH-380-F is the Department of Labor’s FMLA certification for an employee who needs time off to care for a family member with a serious health condition. Your patient is the family member who is ill, not the employee. Section II is the employee’s. Your part is Section III, pages 2 to 4. The printable PDF is on the Department of Labor’s website.
What is the difference between the WH-380-E and WH-380-F?
The WH-380-E is for an employee’s own health condition, and the WH-380-F is for an employee caring for a family member. On the WH-380-F the patient and the employee are different people, the item numbers differ, and there is no Part C on job functions, because the form is about time to care for someone, not the employee’s job.
Whose name goes on the WH-380-F, the patient or the employee?
Write your patient’s name, the person who is ill, the one in front of you, in Part A, item 1, on page 2. Employee Name, at the top of pages 2, 3 and 4, is the family member who works.
What do I write for the care a family member needs?
In Part A, item 4, of the WH-380-F, describe the care needed, not the diagnosis. The form hands you the vocabulary in its own example list, and those words are worth using because they match the boxes the employee checked in Section II: help with basic medical, hygiene, nutrition or safety needs; transport; physical care; psychological comfort.
Should I fill in Section II if the employee left it blank?
No. Section II of the WH-380-F is the employee’s. If it arrives blank, don’t fill it in yourself, and don’t have your staff call the employee to get the answers. Fill out your part, Section III, as usual, then give the form back and tell your patient that the employee has to complete and sign Section II before it goes to the employer.
Who can I hand the completed WH-380-F to?
To your patient, or to the employee if your patient or whoever properly speaks for them has authorized it. The form says to return it to the patient, and the employee is a different person. My understanding is that the details turn on your state and your practice’s own policy, so raise this with your privacy officer. At the visit I get a signed authorization naming who may receive it. I still give the form back, and I send it to HR only if my patient, or whoever speaks for them, authorized that in writing.